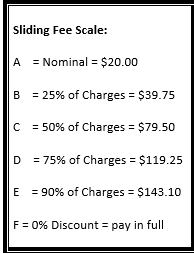
1. Eligibilityfor the William Bee Ririe Hospital and Rural Health Clinic (WBRH/RHC) Sliding FeeScale is dependent on the number of people in your family and your familyincome.
2. Pleasefill out the Sliding Fee Scale Application. Sign and date the application and return it with proof of income toWBRH/RHC Patient Financial Service Representative.
3. PROOFOF INCOME – We need current paycheck stubs or a letter from the company/personthat you work for that reflects one month’s income for ALL applicable householdmembers. If you or any applicablehousehold member receives any other source of income, please provide thatinformation as well.
4. Beloware some examples of other income that you will need to provide:
· Copy of Federalincome tax return
· SocialSecurity, VA Benefits
· Pension,Retirement
· PublicAssistance
· Unemployment
· DisabilityIncome, Workers Compensation
· ChildSupport, Alimony
· Unemployed(Proof of Unemployment form must be completed)
5. Theapplication must be filled out completely, signed, dated, attach proof ofincome and returned to the billing office within 5 business days.
6. AllCo-Payments are required at the time of your office visit.
7. Allapplicants MUST REQUALIFY annually.
8. TheSliding Fee Scale will be reviewed and modified in accordance with the institution’sfiscal accounting system.
9. Recordsof all qualified applicants will be maintained in the WBRH/RHC billing office.
10. If we determine you do not qualify for theSliding Fee Scale or you have not provided proof of income and or proof ofunemployment, you will be responsible for the full billed amount.